
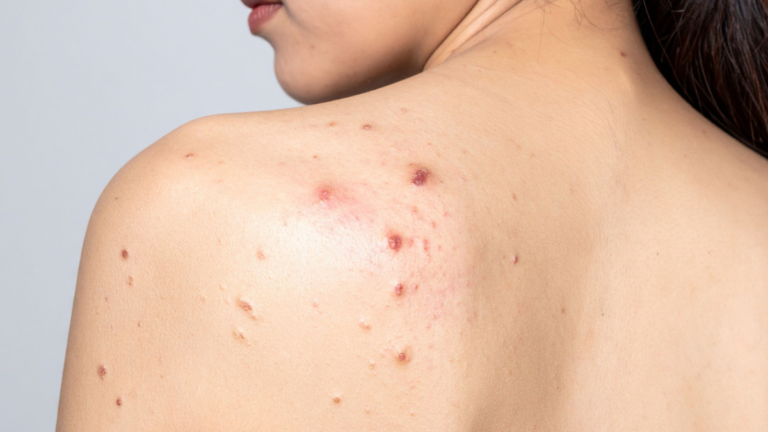

You have small bumps across your chest, shoulders or back. They itch, they flare when you sweat, and every acne wash you have tried either does nothing or makes them worse. Somewhere online you read the word “Demodex” and wondered if mites had spread from your face to your body.
It is a fair question – and the honest answer changes how you treat it. Demodex on the body is real but genuinely uncommon, and the rash that looks most like it on the trunk is usually a yeast, not a mite. Getting that distinction right is the difference between weeks of frustration and skin that finally settles.
Quick answer
Demodex mites concentrate in the oil-rich skin of the face and scalp, so true ‘body demodicosis’ on the chest, back or limbs is uncommon – the deeper mite, Demodex brevis, can reach the upper trunk, but widespread involvement usually signals a run-down immune system. Most itchy bumps on the chest and back are actually Malassezia (yeast) folliculitis, often mistaken for acne. Identifying mites versus yeast versus ordinary acne is the key to clearing them.
|
>5/cm²
density linked with disease
|
0.15 mm
D. brevis, the deeper trunk mite
|
~80%
of yeast folliculitis cases itch
|
Does Demodex live on the body, or just the face?
Two mite species live on human skin. Demodex folliculorum sits in hair follicles, and Demodex brevis – the smaller one, about 0.15 mm – lives deeper in the oil glands and is the species most likely to be found on the upper trunk. Both feed on oil, so they cluster where your skin is oiliest: the face and scalp. That is why, when people search for mites “on the body,” the story almost always leads back to the face first. For the facial picture, see Demodex on the face.

Mites follow the oil. The trunk carries far fewer than the face, and the limbs fewer still.
When body Demodex is actually a concern
Extensive demodicosis beyond the face – crusted or widespread papules on the trunk – is uncommon and tends to appear when local immune control drops: think long-term topical steroids, HIV, diabetes, or immune-suppressing medication. If bumps are spreading widely and behaving aggressively, that is a reason to see a clinician rather than self-treat.
The bigger culprit on the chest and back: yeast
Here is the twist most people miss. The rash that looks like “mite acne” on the upper back and chest is usually Malassezia (yeast) folliculitis – also called fungal acne or Pityrosporum folliculitis. It shows up as small, uniform, dome-shaped pustules, it is often intensely itchy, and it flares with heat, humidity and sweat. Tellingly, it frequently starts or worsens after a course of antibiotics, which clears competing bacteria and lets the yeast bloom.
Because yeast, mites and ordinary acne can look alike, treating the wrong one is the number-one reason chest and back bumps drag on for months. Our guides to Demodex vs yeast folliculitis, seborrheic dermatitis and Demodex, and Demodex and Candida go deeper on the overlap.

Most itchy, uniform pustules on the trunk are yeast; treatment-resistant, rosacea-linked bumps point to mites.
Mites or yeast? Reading the clues
You cannot diagnose from a photo alone, but the pattern usually points one way. Use these cues as a guide, then confirm with a clinician if it is not clearing.

Trunk-based, sweat-driven and very itchy leans yeast; face-first, rosacea-linked and treatment-resistant leans mites.
FOR PRACTITIONERS
Body demodicosis is disproportionately reported in immunosuppression; density >5 mites/cm2 on standardized skin surface biopsy supports pathogenicity. On the trunk, weigh Malassezia folliculitis first (monomorphous follicular pustules, upper back/chest, pruritus in ~80%, post-antibiotic onset) – direct examination of expressed follicular contents distinguishes yeast from mites. Empirical antibiotics can worsen Malassezia folliculitis.
How to calm body bumps
The steps are simple once the driver is clear. Cleanse gently without stripping; match the active to the cause – anti-yeast support for Malassezia, acaricidal support such as terpinen-4-ol for mites; avoid reaching for more antibiotics, which can feed yeast; and rebuild the barrier over several weeks. The natural remedies review and the research hub cover the evidence.
Not sure if mites are part of your picture?
Map your pattern in two minutes with the free Demodex quiz, or find help through the practitioner directory.
Frequently asked questions
Can you get Demodex on your body, not just your face?
Yes, but it is uncommon. Mites concentrate in the oil-rich skin of the face and scalp; the deeper species, Demodex brevis, can reach the upper trunk. Widespread body involvement is unusual and is more likely when the immune system is run down. Most chest and back bumps are something else.
Is it Demodex or fungal acne on my chest and back?
Usually fungal acne. Uniform, very itchy little pustules across the upper back, chest and shoulders – especially after sweating, heat or a course of antibiotics – point to Malassezia (yeast) folliculitis, not mites. See our guide to Demodex versus yeast folliculitis.
Why do itchy bumps on my back not clear with acne products?
Because they may not be acne. Malassezia folliculitis and, less often, Demodex both resist ordinary acne treatments and sometimes worsen with antibiotics. Identifying the real driver is the fastest route to clear skin – the testing guide explains how.
Can Demodex spread from my face to my body?
Mites can be present in follicles beyond the face, but they do not usually ‘spread’ the way an infection does – they overgrow where conditions favour them. Managing facial density and supporting the barrier is the practical goal.
How do I get rid of body bumps for good?
First get the diagnosis right, because yeast, mites and ordinary acne are treated differently. From there, gentle cleansing, the right anti-yeast or acaricidal support, and barrier care over several weeks is what holds results. Start with the free quiz.
References
- Pathology Outlines. Demodex (D. brevis, 0.15-0.2 mm, upper trunk). pathologyoutlines.com
- Demodex folliculitis (density >5/cm2; extension in immunocompromise). CMAJ. PMC5489393
- Malassezia folliculitis: pathogenesis and diagnostic challenges. 2024. PMC11633069
- Malassezia (Pityrosporum) folliculitis: upper back, chest, arms; ~80% pruritus. PMC6993079
- Karabay EA, Cerman AA. Demodex in facial dermatoses (SD affecting chest/back). 2020. PMC7175027
- DermNet. Malassezia folliculitis. dermnetnz.org
About the author. Marina Ivakhnenko is a functional skin practitioner focused on Demodex-related skin conditions. This article is educational and is not a substitute for medical diagnosis or care.


