
Demodex Diagnosis is becoming increasingly important in modern dermatology due to the strong association between Demodex infestation and chronic inflammatory skin disorders. Demodex mites are microscopic ectoparasites that inhabit the pilosebaceous units of human skin. The two primary species identified in humans are Demodex folliculorum and Demodex brevis. While these mites are considered part of the normal skin microbiota in low densities, abnormal proliferation has been associated with multiple inflammatory skin disorders, particularly rosacea, demodicosis, blepharitis, seborrheic dermatitis, and acneiform eruptions.
In recent years, interest in Demodex-associated skin disease has significantly increased due to improved diagnostic techniques and growing evidence linking high mite density to chronic inflammatory dermatological conditions.
Understanding Demodex Infestation and Colonization
Demodex mites mainly colonize areas rich in sebaceous glands, including:
- Forehead
- Nose
- Cheeks
- Chin
- Eyelids
- Scalp
The mites feed on sebum, epithelial cells, and follicular debris. Their population tends to increase with age, immunosuppression, excessive sebaceous activity, chronic inflammation, and altered skin barrier function.
Although Demodex can exist asymptomatically, excessive colonization may trigger:
- Mechanical follicular obstruction
- Inflammatory immune responses
- Bacterial proliferation
- Hypersensitivity reactions
Researchers have also suggested that Demodex mites may carry bacteria such as Bacillus oleronius, which can contribute to inflammation in rosacea patients.
Clinical Signs and Symptoms
The diagnosis of demodicosis is often challenging because clinical manifestations overlap with several common skin diseases.
Typical symptoms include:
Cutaneous Symptoms
- Persistent facial redness
- Papules and pustules
- Dry and rough skin texture
- Burning sensation
- Itching and irritation
- Increased skin sensitivity
- Follicular scaling
- Flushing episodes
- Acne-like lesions resistant to conventional treatment
Ocular Symptoms
Ocular demodicosis commonly affects the eyelids and eyelashes and may present with:
- Chronic blepharitis
- Eyelash crusting
- Foreign body sensation
- Dry eye syndrome
- Eyelash loss
- Eye itching
- Recurrent chalazion
Cylindrical dandruff around eyelashes is considered one of the most characteristic clinical findings in ocular Demodex infestation.
Diagnostic Techniques for Demodex Detection
1. Standardized Skin Surface Biopsy (SSSB)
Standardized Skin Surface Biopsy remains one of the most accepted methods for evaluating Demodex density.
Procedure
A drop of cyanoacrylate glue is placed on a microscope slide and applied to the affected skin area for approximately one minute. The slide is then removed, collecting superficial follicular contents for microscopic examination.
Diagnostic Threshold
A density greater than 5 mites/cm² is generally considered pathological and suggestive of demodicosis.
Advantages
- Quantitative assessment
- High diagnostic accuracy
- Widely used in clinical studies
- Useful for treatment monitoring
Limitations
- Mild discomfort
- Requires microscopy
- Sampling variability between skin regions
Several comparative studies have shown SSSB to have greater sensitivity than direct microscopic examination.
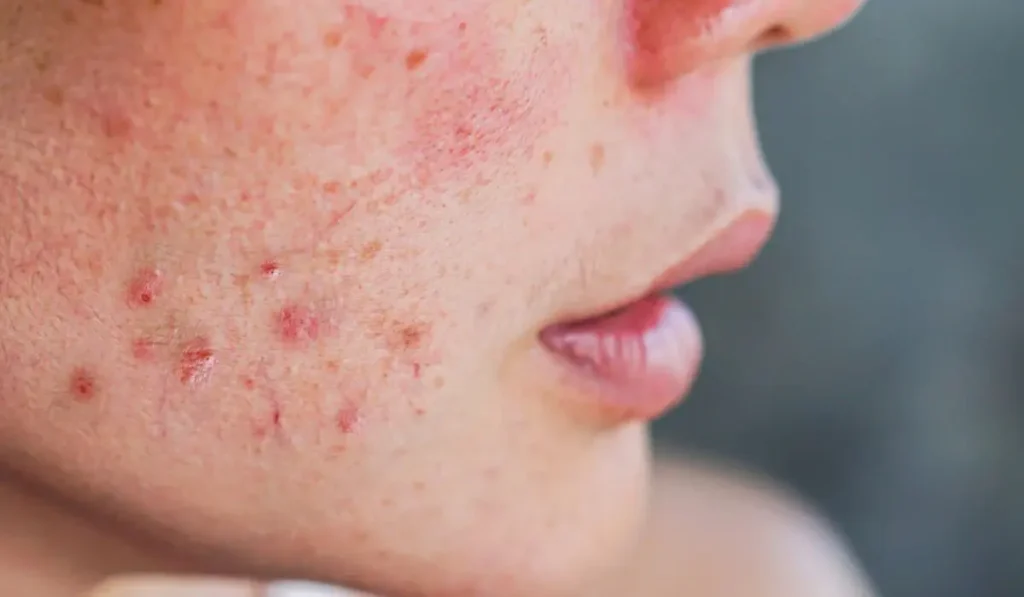
2. Direct Microscopic Examination (DME)
Direct microscopic examination involves expressing follicular material from the skin using gentle pressure.
The sample is mixed with potassium hydroxide or immersion oil and examined under a microscope.
Advantages
- Rapid procedure
- Simple equipment requirements
- Low cost
Disadvantages
- Lower sensitivity
- Operator-dependent
- Less standardized than SSSB
3. Demodex Diagnosis Using Dermoscopy
Dermoscopy is increasingly recognized as a valuable non-invasive tool for diagnosing Demodex-related disorders.
Characteristic Dermoscopic Findings
- Demodex tails protruding from follicles
- White gelatinous threads
- Follicular plugs
- Enlarged follicular openings
- Scaling around follicles
- Telangiectatic vessels
In rosacea patients, dermoscopy may reveal polygonal vascular patterns associated with inflammatory changes.
Dermoscopy offers rapid chairside evaluation and may reduce the need for invasive sampling in selected patients.
4. Reflectance Confocal Microscopy (RCM)
Reflectance Confocal Microscopy allows real-time visualization of mites within follicles without skin sampling.
Benefits
- Non-invasive
- High-resolution imaging
- Useful for repeated follow-up
Limitations
- Expensive equipment
- Limited availability
- Requires trained personnel
RCM is currently more common in research and specialized dermatology centers.
5. Polymerase Chain Reaction (PCR)
Molecular diagnostic techniques such as PCR have recently emerged as highly sensitive methods for detecting Demodex DNA.
PCR may be particularly useful in:
- Low-density infestations
- Research applications
- Comparative diagnostic studies
Recent publications suggest PCR may improve diagnostic sensitivity compared to traditional microscopy. Modern Demodex Diagnosis methods continue to improve diagnostic accuracy in dermatology.
Differential Diagnosis
Demodicosis should be differentiated from:
- Acne vulgaris
- Papulopustular rosacea
- Seborrheic dermatitis
- Perioral dermatitis
- Allergic contact dermatitis
- Lupus erythematosus
- Bacterial folliculitis
Failure to recognize Demodex involvement may result in prolonged ineffective treatment.
Importance of Early Diagnosis
Early and accurate diagnosis is important because untreated Demodex overgrowth may contribute to chronic inflammation and worsening skin barrier dysfunction.
Patients with resistant rosacea or recurrent inflammatory facial eruptions should be evaluated for Demodex infestation, especially when conventional therapies fail.
Early identification also allows clinicians to monitor treatment response objectively through mite density reduction.
Conclusion
Demodex mites play an increasingly recognized role in inflammatory skin disease. Advances in dermoscopy, microscopy, and molecular diagnostics have improved the ability of clinicians to identify clinically significant infestations.
Among current methods, Standardized Skin Surface Biopsy remains the most widely accepted quantitative technique, while dermoscopy offers a rapid and non-invasive complementary approach.
Improved awareness of Demodex-associated disease can lead to earlier diagnosis, more targeted treatment strategies, and better long-term outcomes for patients with chronic inflammatory dermatoses. Early Demodex Diagnosis may help prevent chronic inflammatory skin complications.
References
- Forton FMN, De Maertelaer V. Two Consecutive Standardized Skin Surface Biopsies: An Improved Sampling Method to Evaluate Demodex Density as a Diagnostic Tool for Rosacea and Demodicosis. Acta Derm Venereol. 2017;97(2):242-248.
- Aşkin U, Seçkin D. Comparison of standardized skin surface biopsy and direct microscopic examination in Demodex diagnosis. Br J Dermatol. 2010;162(5):1124-1126.
- Fromstein SR, et al. Demodex Blepharitis: Clinical Perspectives. Clin Optom (Auckl). 2018;10:57-63.
- Kara YA, et al. Dermoscopic Findings in Rosacea and Demodicosis. Skin Appendage Disord. 2021.
- Serarslan G, et al. Dermoscopic features of rosacea associated with Demodex infestation. Dermatol Pract Concept. 2021.
- Trave I, et al. Detection of Demodex mites in papulopustular rosacea using PCR and microscopy. Arch Dermatol Res. 2024.
- Aktaş Karabay E, et al. The role of Demodex folliculorum in dermatological diseases. J Cosmet Dermatol. 2020.
- Zhao YE, et al. Association between Demodex infestation and rosacea: A meta-analysis. J Zhejiang Univ Sci B. 2012;13(3):192-202.


