
Introduction
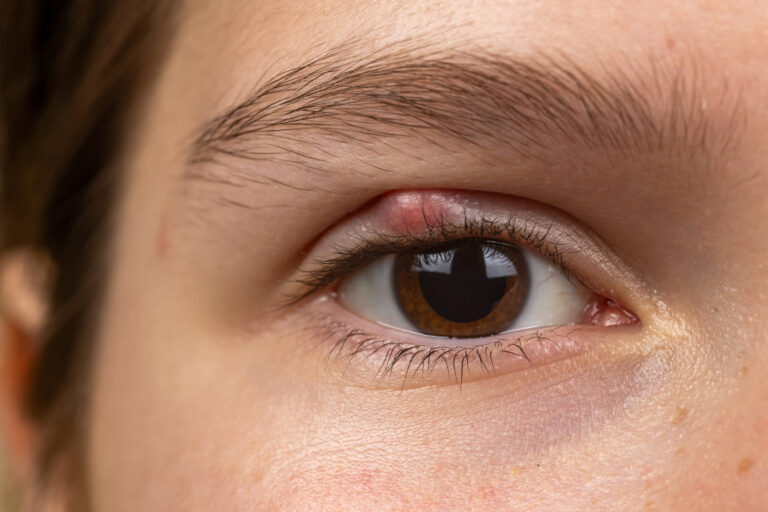
Demodex Chalazion is increasingly recognized as an important cause of recurrent eyelid inflammation and meibomian gland dysfunction. A chalazion is one of the most common eyelid disorders encountered by ophthalmologists and optometrists. It appears as a localized swelling or lump within the eyelid and develops when a meibomian gland becomes blocked and inflamed. While many chalazia resolve with conservative treatment, some patients experience recurrent or persistent lesions that repeatedly return despite medical intervention.
Recent studies have highlighted a potential relationship between recurrent chalazion and Demodex mite infestation. Demodex mites are microscopic ectoparasites that inhabit human skin and hair follicles, including eyelashes and meibomian glands. Growing evidence suggests that these mites may contribute to chronic eyelid inflammation, meibomian gland dysfunction, and the development of recurrent chalazia.
Understanding this connection is important because treating the underlying Demodex infestation may significantly reduce recurrence rates and improve overall eyelid health.
What Is a Chalazion?
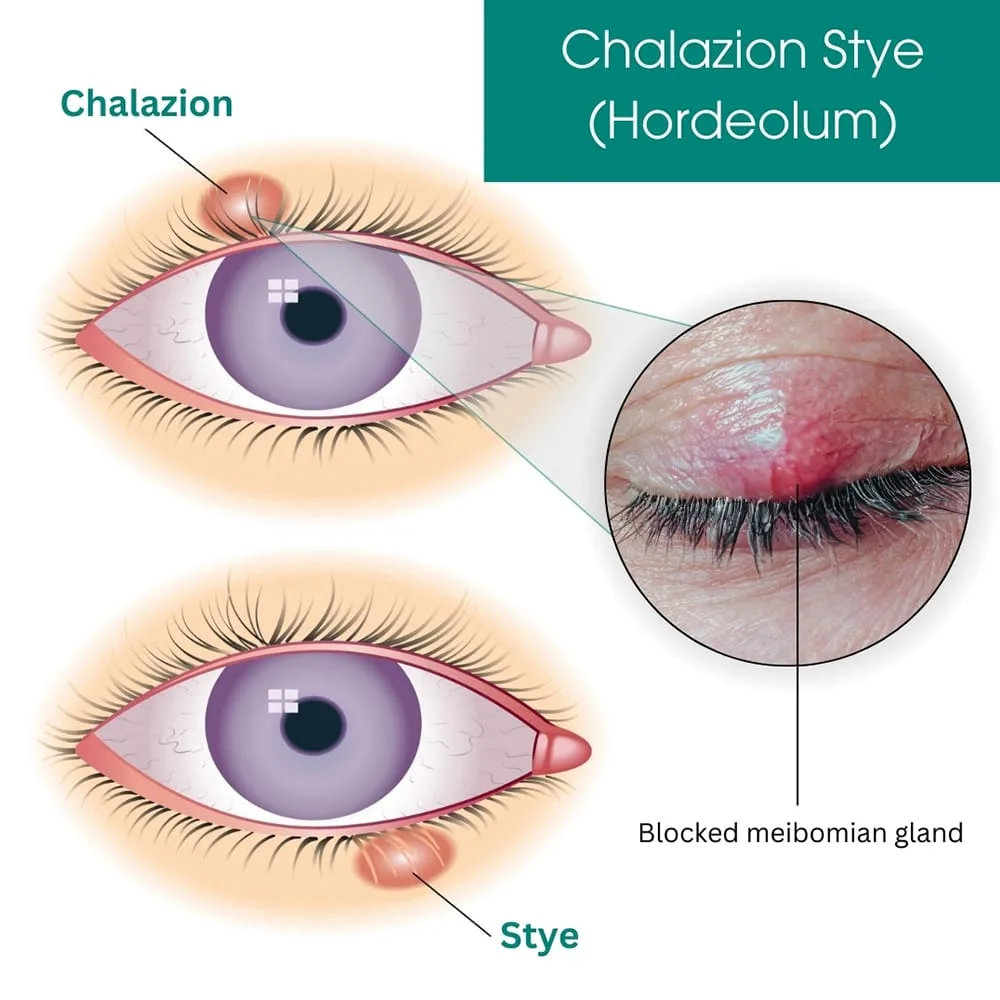
A chalazion is a chronic inflammatory lesion that develops when a meibomian gland becomes obstructed.
The meibomian glands are specialized oil-producing glands located within the eyelids. Their primary function is to secrete lipids that form the outer layer of the tear film, helping prevent excessive tear evaporation and maintaining ocular comfort.
When the gland becomes blocked:
- Oil accumulates inside the gland.
- The gland enlarges.
- Inflammatory cells infiltrate the area.
- A firm lump develops within the eyelid.
Unlike a stye (hordeolum), a chalazion is typically not caused by an active bacterial infection.
Common Symptoms
Patients with chalazion may experience:
- Localized eyelid swelling
- A painless lump inside the eyelid
- Mild eyelid tenderness
- Blurred vision if the lesion becomes large
- Cosmetic concerns
- Eyelid heaviness
Large chalazia may exert pressure on the cornea and induce temporary astigmatism, leading to visual disturbances.
Understanding Demodex Mites
Demodex mites are tiny parasites that naturally inhabit human skin.
The two species most commonly found on humans are:
Demodex folliculorum
This species primarily inhabits hair follicles, especially those associated with eyelashes.
Demodex brevis
This species lives deeper within sebaceous glands and meibomian glands.
Although Demodex mites are considered part of the normal skin microbiome, excessive populations can trigger inflammatory reactions and contribute to several dermatological and ophthalmological conditions.
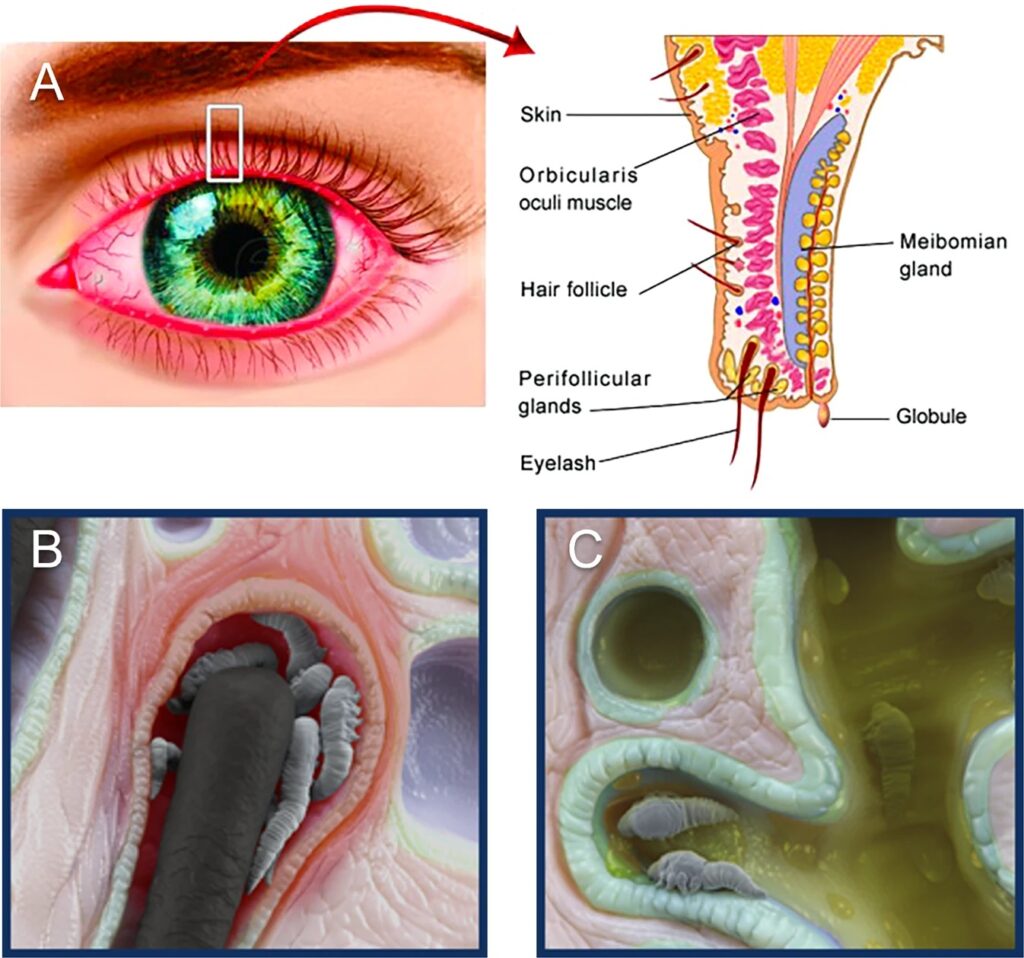
A Overview schematic of eyelash and gland structures. B Demodex folliculorum mites located within the lash follicle. C Demodex brevis mites located within the meibomian gland.
Demodex and Eyelid Disease
Researchers have increasingly recognized Demodex as an important contributor to ocular surface disorders.
Demodex infestation has been associated with:
- Chronic blepharitis
- Meibomian gland dysfunction
- Dry eye disease
- Ocular rosacea
- Keratitis
- Recurrent chalazion
Patients with recurrent eyelid problems often exhibit significantly higher Demodex counts than healthy individuals.
How Demodex Causes Chalazion
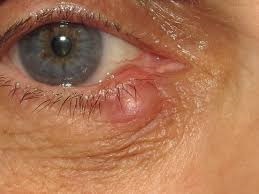
Several mechanisms may explain how Demodex contributes to chalazion formation.The relationship between Demodex Chalazion and meibomian gland blockage has been reported in several clinical studies.
1. Mechanical Obstruction of Meibomian Glands
Demodex brevis resides directly within the meibomian glands.
As mite populations increase, they may physically obstruct gland openings and interfere with normal oil secretion.
The resulting blockage creates ideal conditions for chalazion development.
2. Chronic Inflammatory Response
Demodex mites contain proteins and waste products capable of triggering immune responses.
The body reacts by producing:
- Cytokines
- Inflammatory mediators
- Immune cell infiltration
Persistent inflammation damages gland tissue and increases the likelihood of recurrent blockage.
3. Bacterial Transmission
Demodex mites may carry bacteria on their surface.
Some studies suggest they transport microorganisms such as:
- Bacillus species
- Staphylococcus species
These bacteria may enhance inflammatory reactions and worsen eyelid disease.
4. Altered Meibomian Gland Function
Demodex infestation has been linked to:
- Reduced gland secretion
- Increased meibum viscosity
- Gland dropout
- Abnormal gland morphology
These changes contribute directly to chalazion formation.
Scientific Evidence Linking Demodex and Chalazion
Multiple studies have demonstrated a higher prevalence of Demodex infestation among patients with recurrent chalazia.
Researchers have reported that:
- Patients with recurrent chalazion frequently exhibit higher Demodex counts.
- Demodex-positive individuals often show more severe meibomian gland dysfunction.
- Treating Demodex infestation may reduce recurrence rates following chalazion removal.
These findings suggest that Demodex infestation should be considered whenever patients experience repeated eyelid lumps.
Signs Suggesting Demodex Involvement
Certain clinical findings may indicate an underlying Demodex infestation.
Cylindrical Dandruff
The most characteristic sign is cylindrical dandruff at the base of eyelashes.
These sleeve-like deposits consist of:
- Keratin
- Sebum
- Mite waste products
Their presence strongly suggests Demodex infestation.
Eyelid Itching
Patients frequently report itching that is worse:
- In the morning
- Upon waking
Chronic Blepharitis
Persistent eyelid inflammation often accompanies Demodex infestation.
Dry Eye Symptoms
Patients may experience:
- Burning
- Foreign body sensation
- Redness
- Excessive tearing
Recurrent Chalazia
Multiple chalazia occurring over months or years should raise suspicion for Demodex involvement.
Diagnosis
Slit-Lamp Examination
Eye care professionals carefully examine:
- Eyelid margins
- Eyelashes
- Meibomian gland openings
Characteristic findings may suggest Demodex infestation. Early diagnosis of Demodex Chalazion may help prevent recurrent eyelid lesions and chronic inflammation.
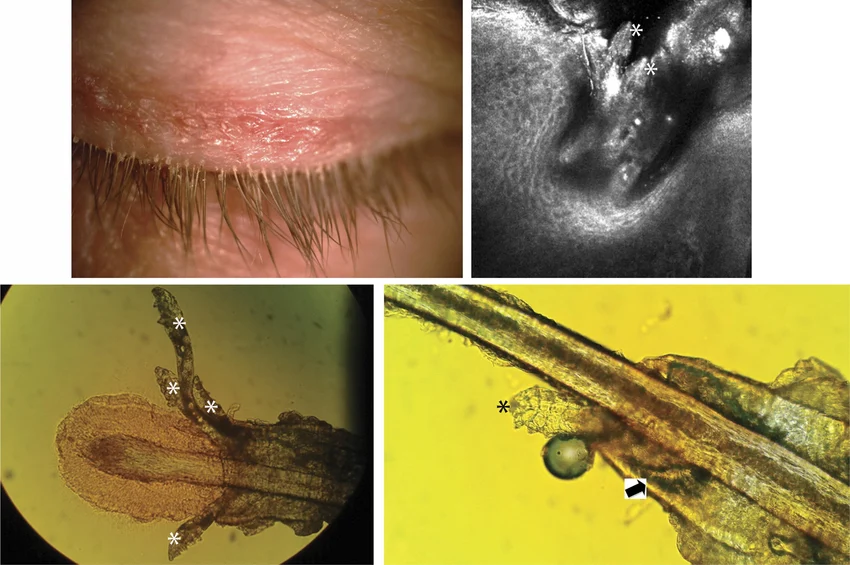
Eyelash Sampling
Several eyelashes may be removed and examined microscopically.
The presence of mites confirms the diagnosis.
Meibography
Advanced imaging techniques allow visualization of meibomian gland structure.
Meibography may reveal:
- Gland dropout
- Shortened glands
- Distorted gland architecture
How to Treat Demodex Chalazion
Warm Compresses
Warm compresses remain the first-line treatment.
Heat helps:
- Soften gland secretions
- Improve drainage
- Reduce inflammation
Eyelid Massage
Gentle massage following warm compresses may facilitate gland emptying.
Topical Medications
Depending on the clinical situation, physicians may prescribe:
- Antibiotic ointments
- Anti-inflammatory medications
Steroid Injection
Persistent chalazia may respond to intralesional corticosteroid injection.
Surgical Removal
Large or chronic lesions may require incision and curettage.
Treating Demodex Infestation
Successful management of recurrent chalazion often requires addressing Demodex mites.
Tea Tree Oil-Based Products
Tea tree oil has demonstrated activity against Demodex mites.
Professional eyelid scrubs and cleansers containing tea tree oil may reduce mite populations.
Lid Hygiene
Daily eyelid cleansing helps remove:
- Debris
- Excess oil
- Cylindrical dandruff
Professional In-Office Treatments
Eye care providers may perform specialized procedures targeting Demodex infestation.
Long-Term Maintenance
Regular eyelid hygiene is often necessary to prevent reinfestation.
Prevention Strategies
Patients can reduce the risk of chalazion recurrence by:
- Maintaining excellent eyelid hygiene
- Managing blepharitis promptly
- Treating Demodex infestations
- Replacing eye makeup regularly
- Avoiding sharing cosmetics
- Attending routine eye examinations
When Should You See an Eye Doctor?
Seek professional evaluation if you experience:
- Recurrent chalazia
- Persistent eyelid swelling
- Significant pain
- Vision changes
- Chronic eyelid irritation
- Signs of Demodex infestation
Early diagnosis can prevent complications and improve treatment outcomes. Proper treatment of Demodex Chalazion should address both the chalazion itself and the underlying Demodex infestation.
Conclusion
Demodex Chalazion represents an important clinical condition that may contribute to recurrent eyelid disease and meibomian gland dysfunction. While chalazion has traditionally been viewed as a simple blockage of the meibomian glands, research increasingly suggests that Demodex mites may play an important role in its development and recurrence. Through gland obstruction, chronic inflammation, bacterial transmission, and meibomian gland dysfunction, Demodex infestation can create conditions that favor chalazion formation.
For patients experiencing recurrent chalazia, evaluation for Demodex infestation may provide valuable diagnostic information and lead to more effective long-term treatment strategies. Addressing both the chalazion and the underlying mite population offers the best chance of preventing recurrence and maintaining healthy eyelids.
Demodex Chalazion is increasingly recognized as a significant factor in recurrent eyelid disease. Early identification of Demodex Chalazion can help reduce recurrence rates and improve patient outcomes. Clinicians should consider Demodex Chalazion in patients with persistent or recurrent eyelid inflammation.
References
- Ocular demodicidosis as a risk factor of adult recurrent chalazion
- High prevalence of Demodex brevis infestation in chalazia
- The association of Demodex infestation with pediatric chalazia
- Ocular Demodicosis as a Potential Cause of Ocular Surface Inflammation
- Demodex blepharitis: clinical perspectives
- Clinical diagnosis and management of Demodex blepharitis
- Demodex Blepharitis: A Comprehensive Review of the Disease, Current Management, and Emerging Therapies


